




U.S.-Based
Prior Authorization Software Development
Prior authorization software development by SoftDoes: custom ePA and utilization management tools with FHIR APIs, built for CMS-0057-F.

Let's build together.
Talk with a senior engineer about your product idea, architecture, and what it would take to build it.
90+
Active Client Partnerships
80+ Person
Product & Engineering Team
100%
Your Code & IP Ownership
U.S.-Led
Delivery & Accountability
We understand the challenges you're facing
Why do our staff track hundreds of pending authorizations in spreadsheets, payer portals, and fax inboxes?
A custom prior authorization platform brings every authorization request into a single work queue fed by the EHR, scheduling system, and intake workflows. Instead of toggling between payer portals, fax confirmations, and spreadsheets, authorization specialists see a unified view built on a consistent data model - patients, coverage, orders, authorization requests, required documents, payer decisions, expirations, and appeals all linked together. Real-time status tracking uses event-driven updates from payers, whether those updates arrive via FHIR PAS responses, X12 278 acknowledgments, or portal-based scraping where modern APIs are not yet available. Transparent tracking helps providers manage large numbers of authorization requests efficiently. SoftDoes designs these data flows so every authorization is linked to its scheduled encounter and final claim, meaning missing or expired approvals are caught before care is rendered - not after a denial shows up in the revenue cycle.
The CMS interoperability and prior authorization final rule sets decision deadlines, denial-reason requirements, reporting obligations, and new APIs. How do we comply on time without rebuilding everything?
SoftDoes builds compliance into prior authorization software from the start rather than bolting it on later. That means built-in decision timers - payers must respond to standard PA requests within seven days and expedited requests within 72 hours under CMS-0057-F - with automatic escalation when deadlines approach, structured denial reasons that go beyond generic "not medically necessary" language, and automated feeds for public reporting of prior authorization metrics. The platform supports the full regulatory and standards landscape: the CMS Interoperability and Prior Authorization Final Rule (CMS-0057-F), HIPAA X12 278 transactions, HL7 Da Vinci implementation guides for Coverage Requirements Discovery (CRD), Documentation Templates and Rules (DTR), and Prior Authorization Support (PAS), NCPDP SCRIPT for pharmacy ePA, URAC and NCQA utilization management standards, state gold-carding laws, and HIPAA privacy and security requirements. Every request, decision, reviewer, and timestamp is logged in an immutable audit trail, and role-based access controls, encryption in transit and at rest, and signed business associate agreements align the platform with regulator and accreditor expectations. Compliance requirements are integrated into PA software from the beginning of development - not retrofitted under deadline pressure.
Can new prior authorization software connect to our Epic or athenahealth system and to dozens of payers without breaking scheduling or billing?
EHR integration is central to every prior authorization software project SoftDoes delivers. The architecture is API-first: FHIR and SMART on FHIR for embedding authorization workflows inside the EHR, X12 278 via clearinghouses like Availity, Change Healthcare/Optum, or Waystar, and payer FHIR PAS APIs where available. Where payers still offer only portals or fax, SoftDoes incorporates safe fallback strategies - portal automation or structured manual-exception workflows - while feeding authorization status back into the same unified record. Migration is handled carefully: open authorizations and history are imported, payer rules and service lists are configured payer by payer, testing runs against each payer's endpoint or sandbox, and go-lives are phased by specialty or region so pending requests are never lost. SoftDoes has hands-on experience with EHRs such as Epic, Oracle Health, athenahealth, and eClinicalWorks; pharmacy ePA networks including CoverMyMeds and Surescripts; clinical criteria tools like InterQual and MCG; and dozens of custom payer and clearinghouse integrations.
Why does each prior auth still take our staff an hour, and why are payer reviewers still scrolling through scanned charts page by page?
Manual prior authorization costs healthcare providers in physician and staff time, burnout, and delayed care - 93% of physicians report prior authorization delays patient care, and 89% say it contributes to burnout. SoftDoes runs user-research sessions and workflow shadowing with authorization specialists, schedulers, clinicians, revenue cycle teams, payer nurses, medical directors, and appeals staff before designing a single screen. The result is role-specific UIs: a provider work queue sorted by service date and denial risk, auto-filled request forms pulled from clinical records in the chart, clinician sign-off embedded in the EHR, a payer reviewer workspace that places guidelines and supporting documents side by side, and leadership dashboards showing SLA adherence and authorization volume. Key UX patterns include requirement checks at the moment of ordering, one-click document attachment, clear visual status and expiry banners, and reusable templates for appeals. Custom prior authorization software development avoids the generic one-size-fits-all portal approach and instead matches the way each organization actually works - reducing the time per PA request from an hour to minutes.
Payers change their rules every month, and regulations keep moving. Are we stuck updating everything by hand?
The platform is modular by design: payer rules, services requiring authorization, documentation checklists, routing logic, and decision timers are driven by configuration rather than hard-coded logic. That means internal teams can update rules under lightweight change-control workflows - with full history and rollback - using an admin console rather than opening engineering tickets for every small tweak. SoftDoes designs extension points, feature flags, and versioned APIs so organizations can add new service types (imaging, surgery, DME, behavioral health, medication authorizations), onboard new participating payers, and adopt emerging requirements like state gold-carding programs without destabilizing the platform. Over 30 states are reforming PA processes with unique requirements, and CMS mandates FHIR-based PA APIs by January 1, 2027 - the system must evolve as fast as the regulatory landscape. SoftDoes delivers technical and process documentation so clients own prior authorization rule maintenance day to day, avoiding vendor lock-in for routine changes.
You make the coverage decisions. We engineer the software behind them.

Provider-side prior authorization platforms
Custom prior authorization platforms built around a provider's specialties, payer mix, and EHR - not a generic multi-payer portal that forces staff into extra manual data entry. Modules include automated eligibility checks, "is authorization required?" logic triggered at ordering, auto-filled requests assembled from clinical data and patient demographics, document capture, multi-channel request submission via FHIR PAS, X12 278, or portal automation, real-time status tracking, expiry alerts, and appeals management.
Payer rules engine configurable by service, diagnosis, plan, and site of care
Automatic submission and status updates across FHIR, X12, and portal channels
Tight linkage of authorizations to scheduling and claims to catch missing or expired approvals before services are rendered

Payer-side intake and utilization management
Utilization management software that accepts prior authorization requests from every channel - FHIR PAS, X12 278, delegated portals, fax capture - and normalizes them into a single intake and review workflow integrated with core claims, member eligibility, and provider directory systems. Auto-approval rules handle standard requests that clearly meet medical necessity criteria, while decision timers and escalation paths ensure every request meets CMS-0057-F timelines.
Unified worklists with SLA timers aligned to CMS-0057-F for standard and expedited requests
Reviewer workspace combining structured clinical documentation, guidelines, and supporting documents with a full audit trail
Automated reporting of prior authorization metrics for CMS, state regulators, and accreditation bodies

AI enhanced prior authorization workflows
AI prior authorization software capabilities focused on the prior auth process: extracting relevant clinical notes from unstructured records and PDFs, matching documentation to payer criteria, predicting denial risk before submission, drafting appeal language, and summarizing cases for payer reviewers. Utilizing AI in software helps extract relevant clinical information from unstructured data - and AI-powered tools can increase prior authorization approval rates by 14% while reducing handling time by up to 83%.
Natural language summaries of clinical documentation for provider and payer reviewers
Predictive scoring of approval or denial risk to prioritize staff attention and improve approval accuracy
Smart prompts for missing documents or criteria before submission to reduce avoidable denials
Numbers Don’t Lie
Recent projects showcasing how we design, engineer, and deliver production-ready software solutions.

- Startup
- Real Estate
Our Haus AI
A finance professional turned founder built Our Haus AI, an AI-powered collaborative workspace where homeowners and contractors scope, bid, contract, and document renovation projects together. SoftDoes took her prototype and made it production-ready.- 10XMVP scope delivered
- 2+years Ongoing partnership
- 1Fully owned Platform

- Finance
- Energy
Deepwater Insights
Deepwater Insights delivers proprietary alternative data and niche research on the offshore drilling and energy sector to institutional investors, family offices, and high-net-worth individuals who require coverage that larger firms don't provide.- 100%Brand Continuity
- 2Platform Distribution
- 100%Paywall-Ready Content

- Real Estate
The building buyer
The Building Buyer is a Florida-based real estate investment firm co-founded by Dylan Troiano and Charles Hanlin. They acquire single-family, multifamily, and commercial properties across South Florida and beyond, with a focus on motivated seller opportunities.- 18Weekly hours saved
- 2+Years Ongoing partnership
- 1Fully owned Platform

- Education
- Non-Profit
WOVEN & NICE
Woven is a Spring Valley, NY nonprofit running the NICE program (New Training Inclusive Community Environment) in four Rockland County schools. Their team supports students through restorative practices, mediation, and professional development for teachers and administrators.- 4Schools Served
- 4Weeks to Launch
- 1STTime on Upwork

- Healthcare
CareInTouch
CareInTouch is a Bay Area home health agency providing skilled nursing and therapy services to patients referred from hospitals and clinics. With over 100 staff, they operate in one of the most complex and compliance-driven healthcare markets in the country.- 40% Reduction In Billing Errors
- 100+Staff Operations Managed
- 0Missed Compliance Deadlines

- Startup
Sparkle The Cleaning Service
Sparkle The Cleaning Service is a Detroit-area residential cleaning company with 10 years in business, connecting homeowners with vetted, insured independent cleaners through a subscription-based marketplace platform.- 75% Platform Transparency
- 2XPlatform Growth
- 40%Higher User Retention

- Startup
DineMate
DineMate is a Maryland-based dating and connecting platform built around verified profiles, restaurant reservations, and prepaid dining experiences. Founded to bring back authenticity to how people meet and connect.- 60% Time Saved
- 99%System Reliability
- 40%Higher User Retention

- Healthcare
Prior Authorization AI
Prior Authorization AI is a healthcare automation startup building AI-powered tools to streamline prior authorization for Medicare and Medicaid medical transportation providers in New Jersey.- 16Weekly hours saved
- 63%Admin time reduced
- 43%Fewer submission errors

- Education
Grand Central Language Services
Grand Central Language Services provides translation and interpretation for organizations operating in complex, multilingual environments. As demand grew, internal workflows became harder to manage. SoftDoes built a custom platform to streamline coordination, improve visibility, and support scalable operations.- 72%Workflow Reduction
- 48%Coordination Reduction
- 83%Visibility Increase

- Healthcare
FMY Orthodontics
FMY Orthodontics, a multi-location practice in West Tennessee, partnered with SoftDoes to replace a spreadsheet-based financial workflow with a custom web platform. The goal was to simplify how staff present treatment financing while allowing patients and families to review and complete decisions remotely.- 60%Workflow Reduction
- 75%Remote Adoption
- 5Locations Aligned

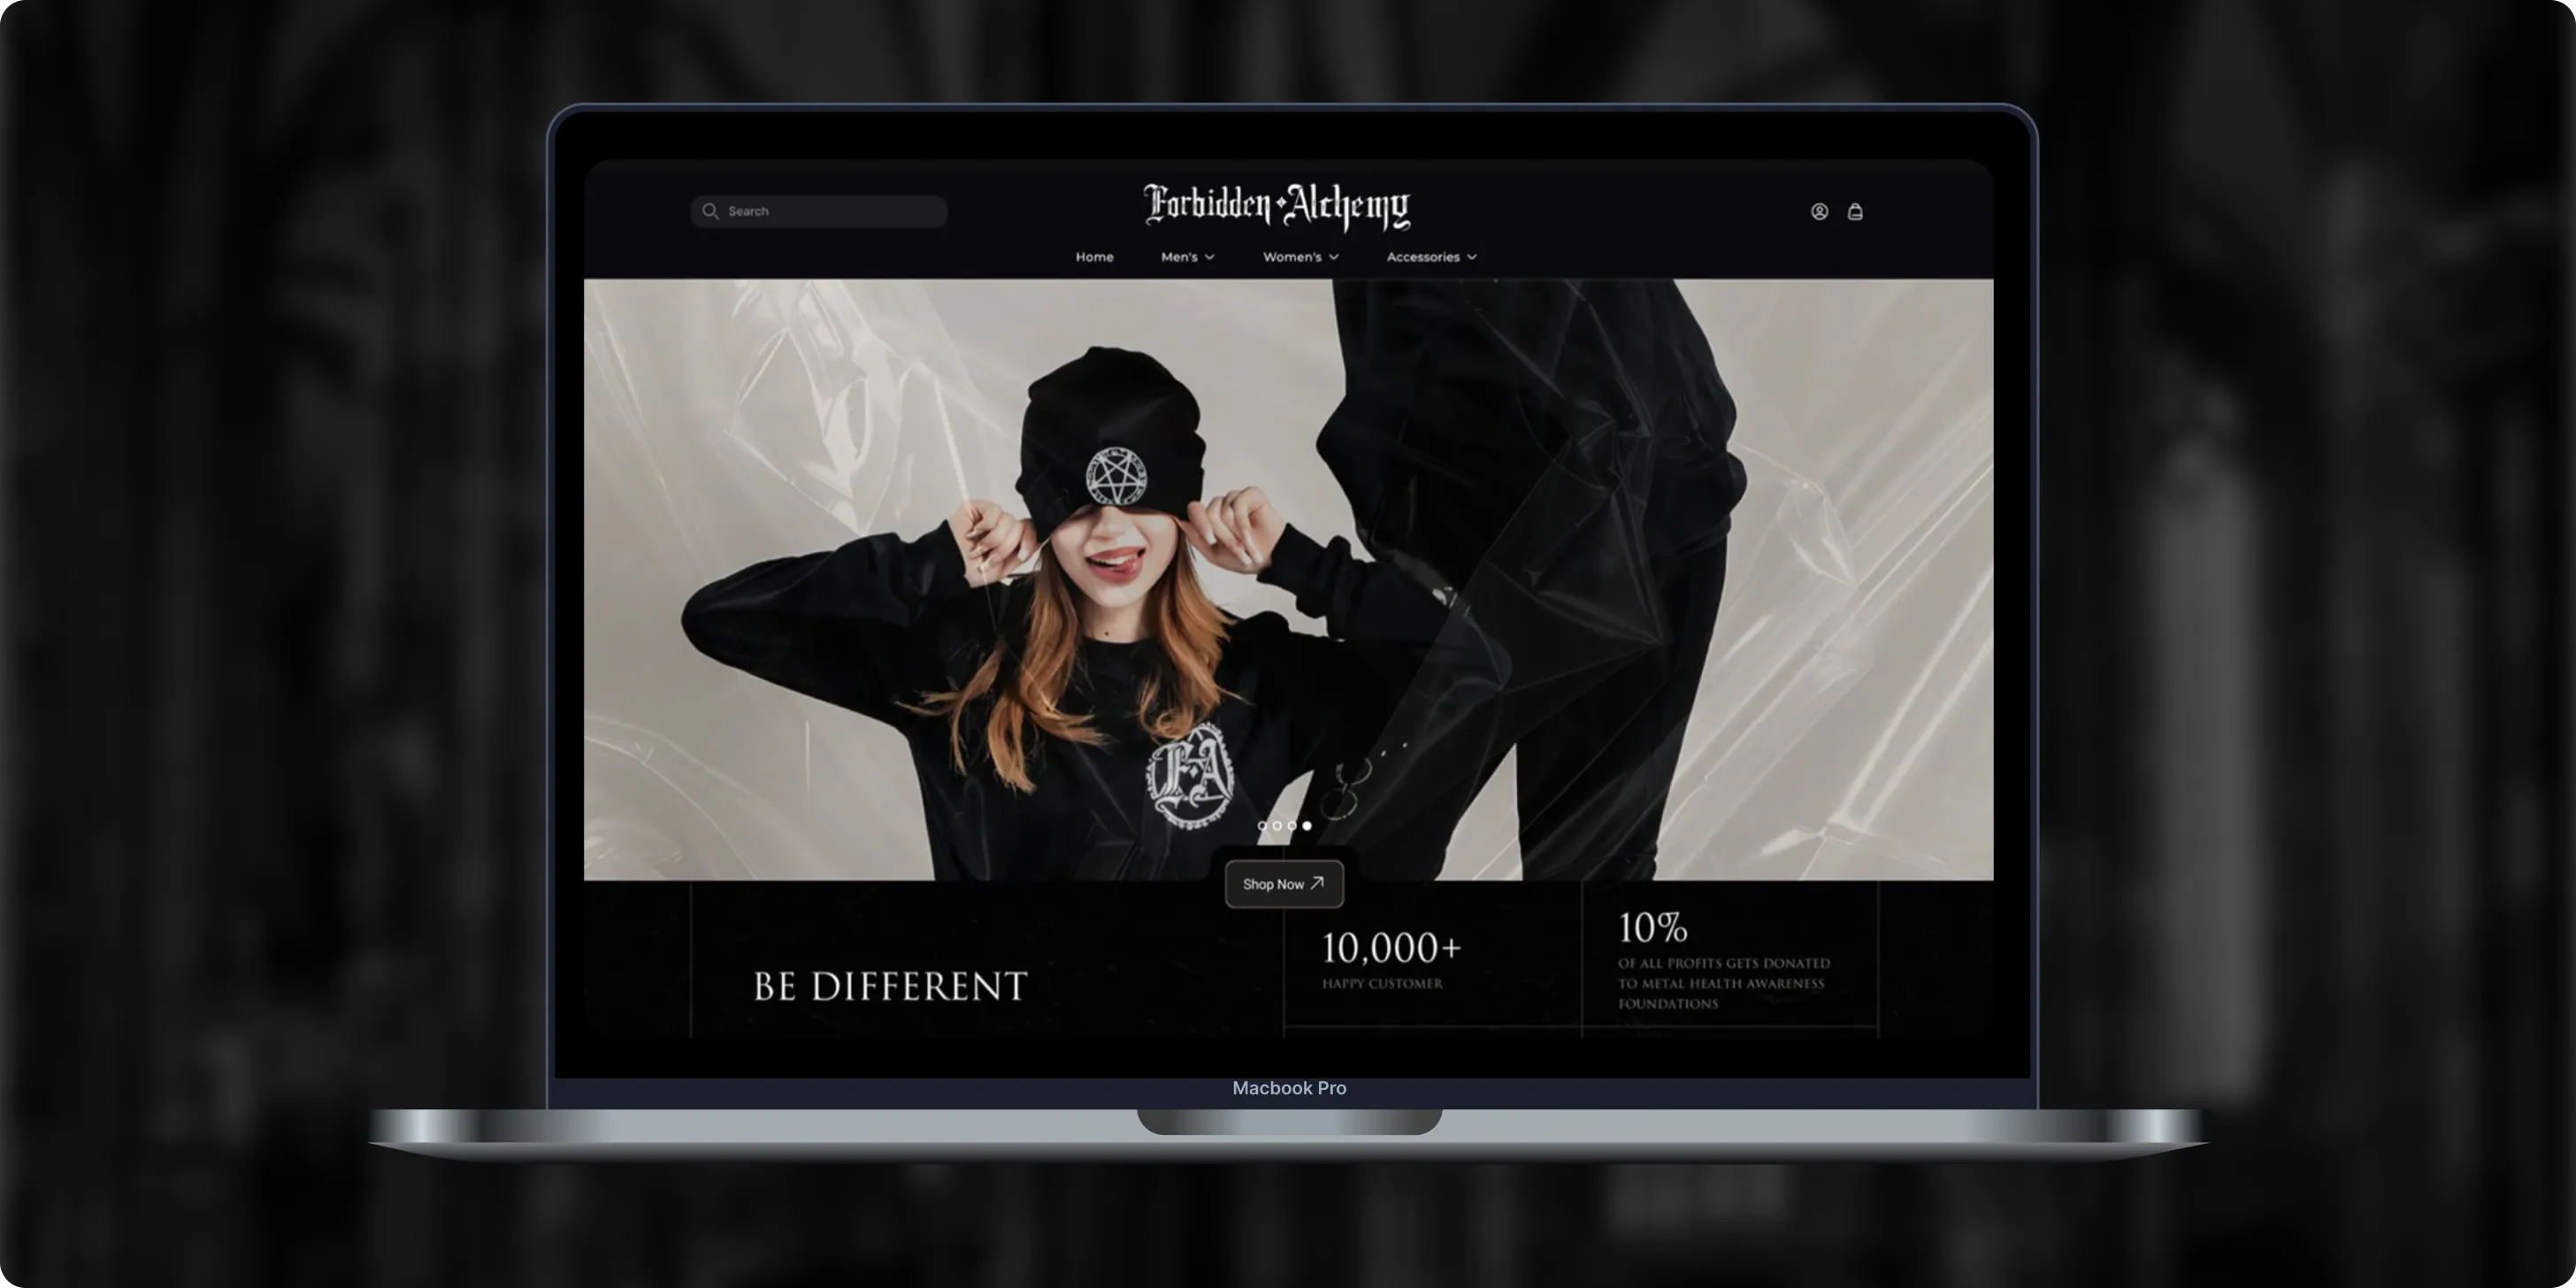
Forbidden Alchemy
Forbidden Alchemy is an alternative fashion brand creating dark, provocative clothing for the metalhead community, with 10% of profits donated to mental health awareness. Its mostly mobile audience struggled with a store that was hard to navigate and weak on functionality.- +44%Revenue Month Over Month
- 86%Design Satisfaction
- 2.8XUser Retention Growth
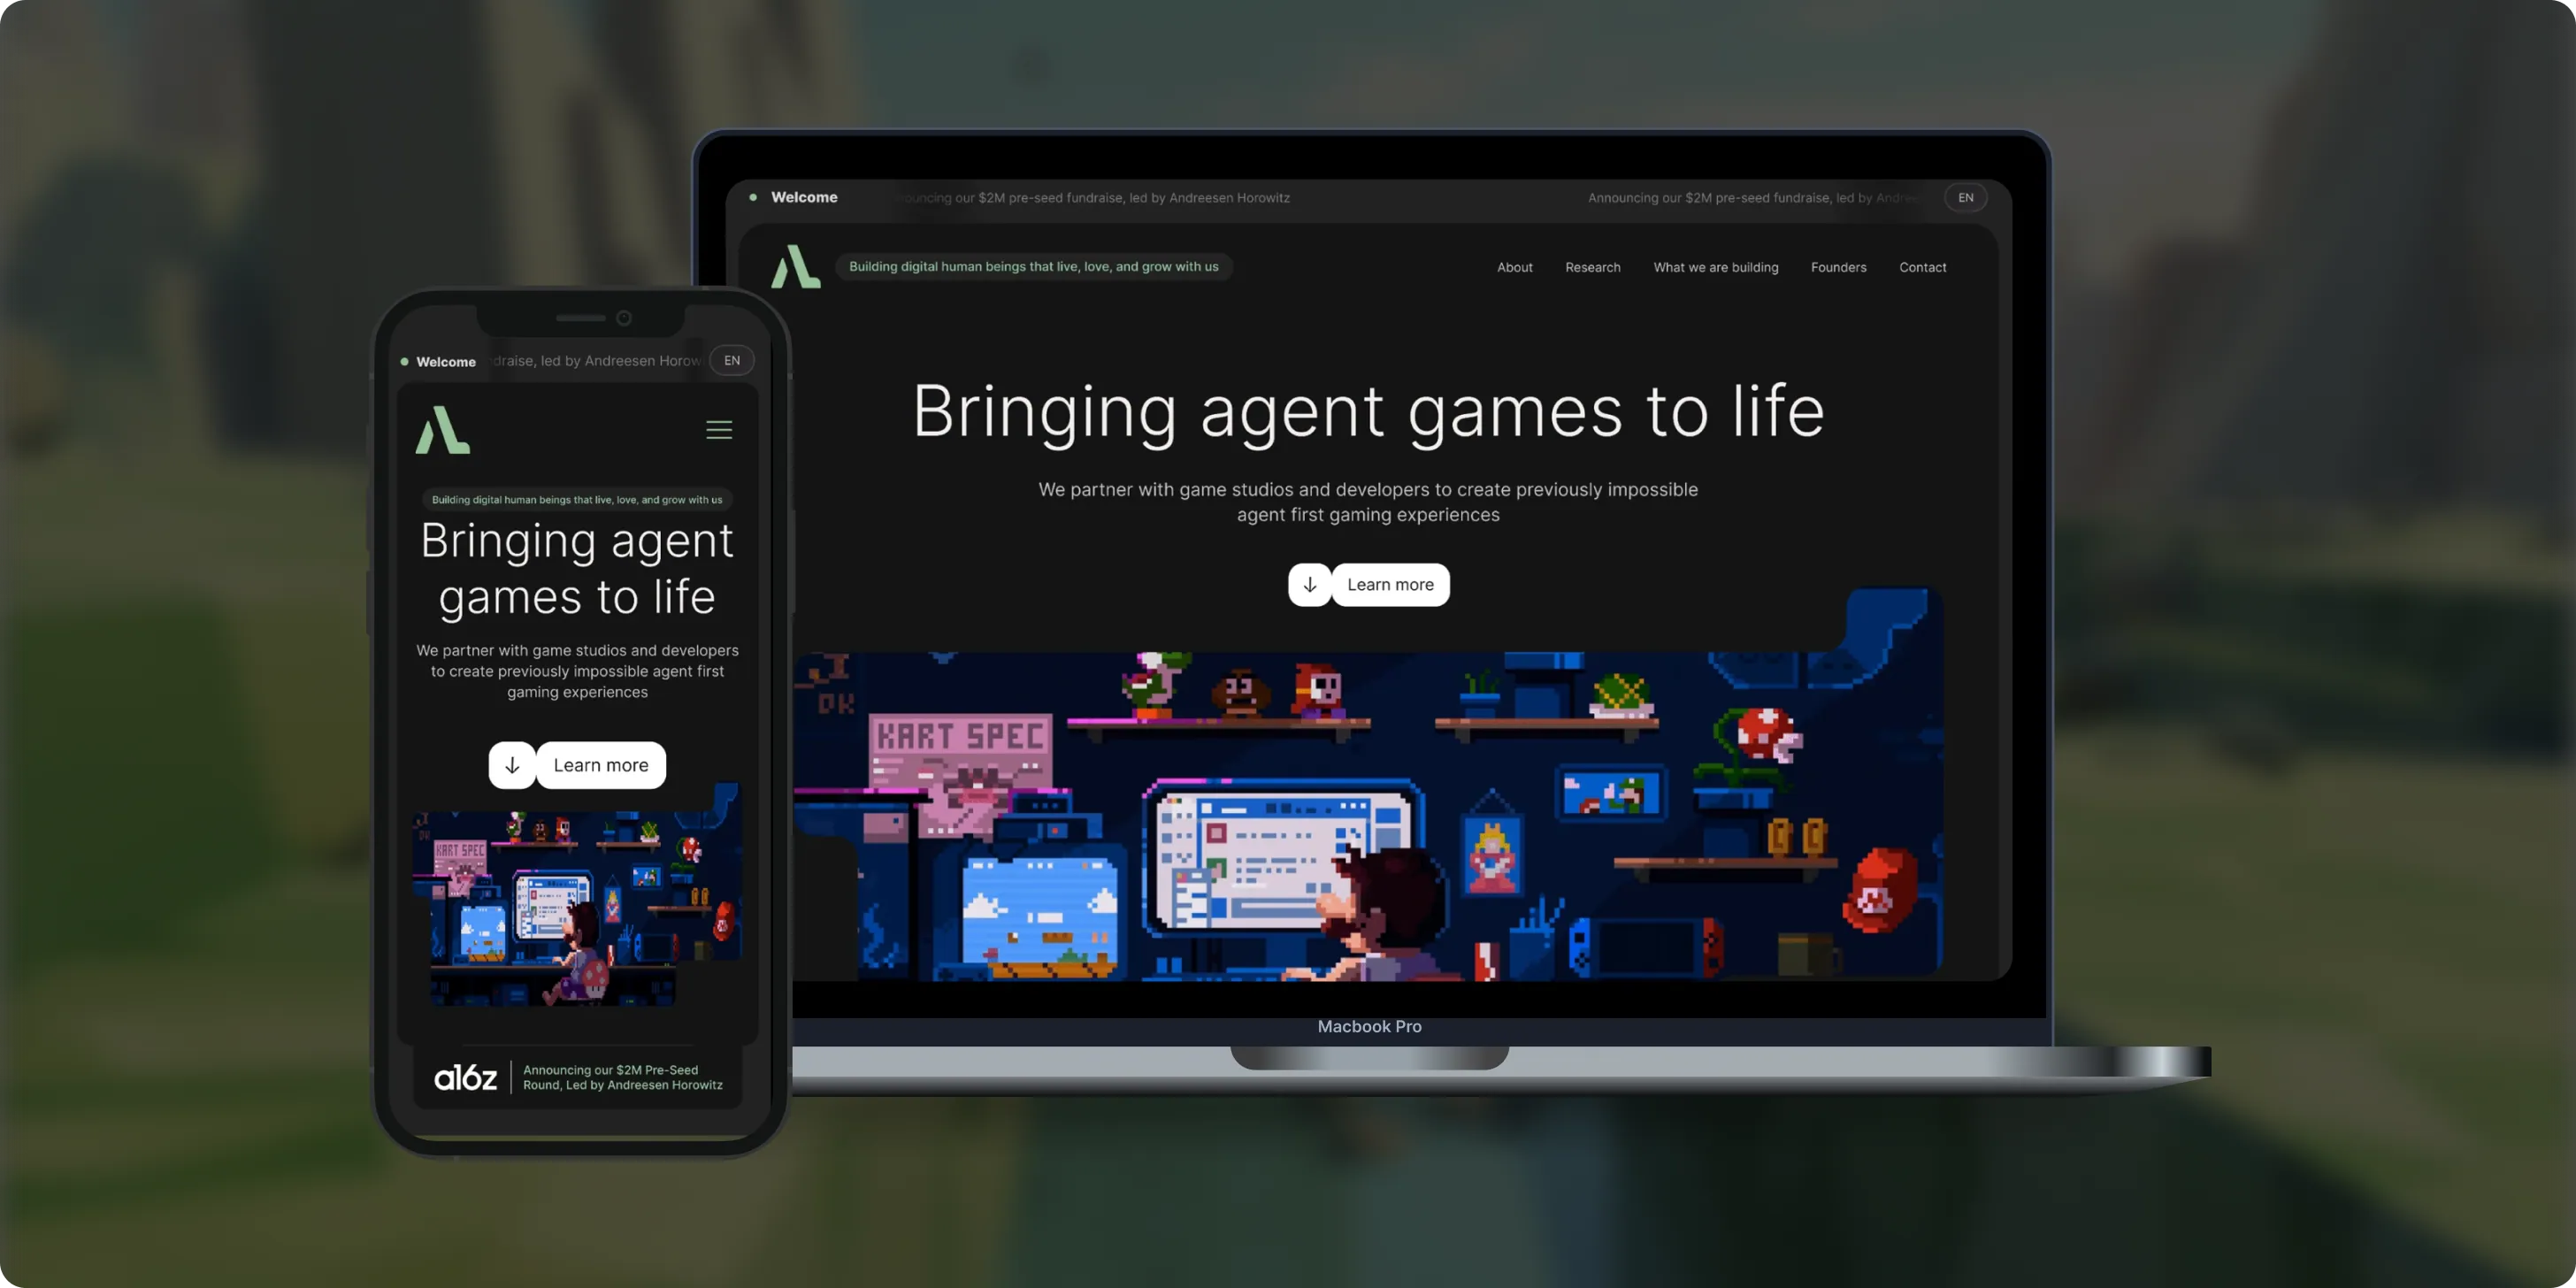
Altera
Altera builds on decades of computational neuroscience research to create digital human beings for gaming. Backed by a $2M pre-seed round led by Andreessen Horowitz, the team needed a landing page that could explain complex agent technology to players, partners, and investors.- 98%Dynamic Customization
- 100%Streamlined Navigation
- $2MPre-Seed Round
- Real Estate
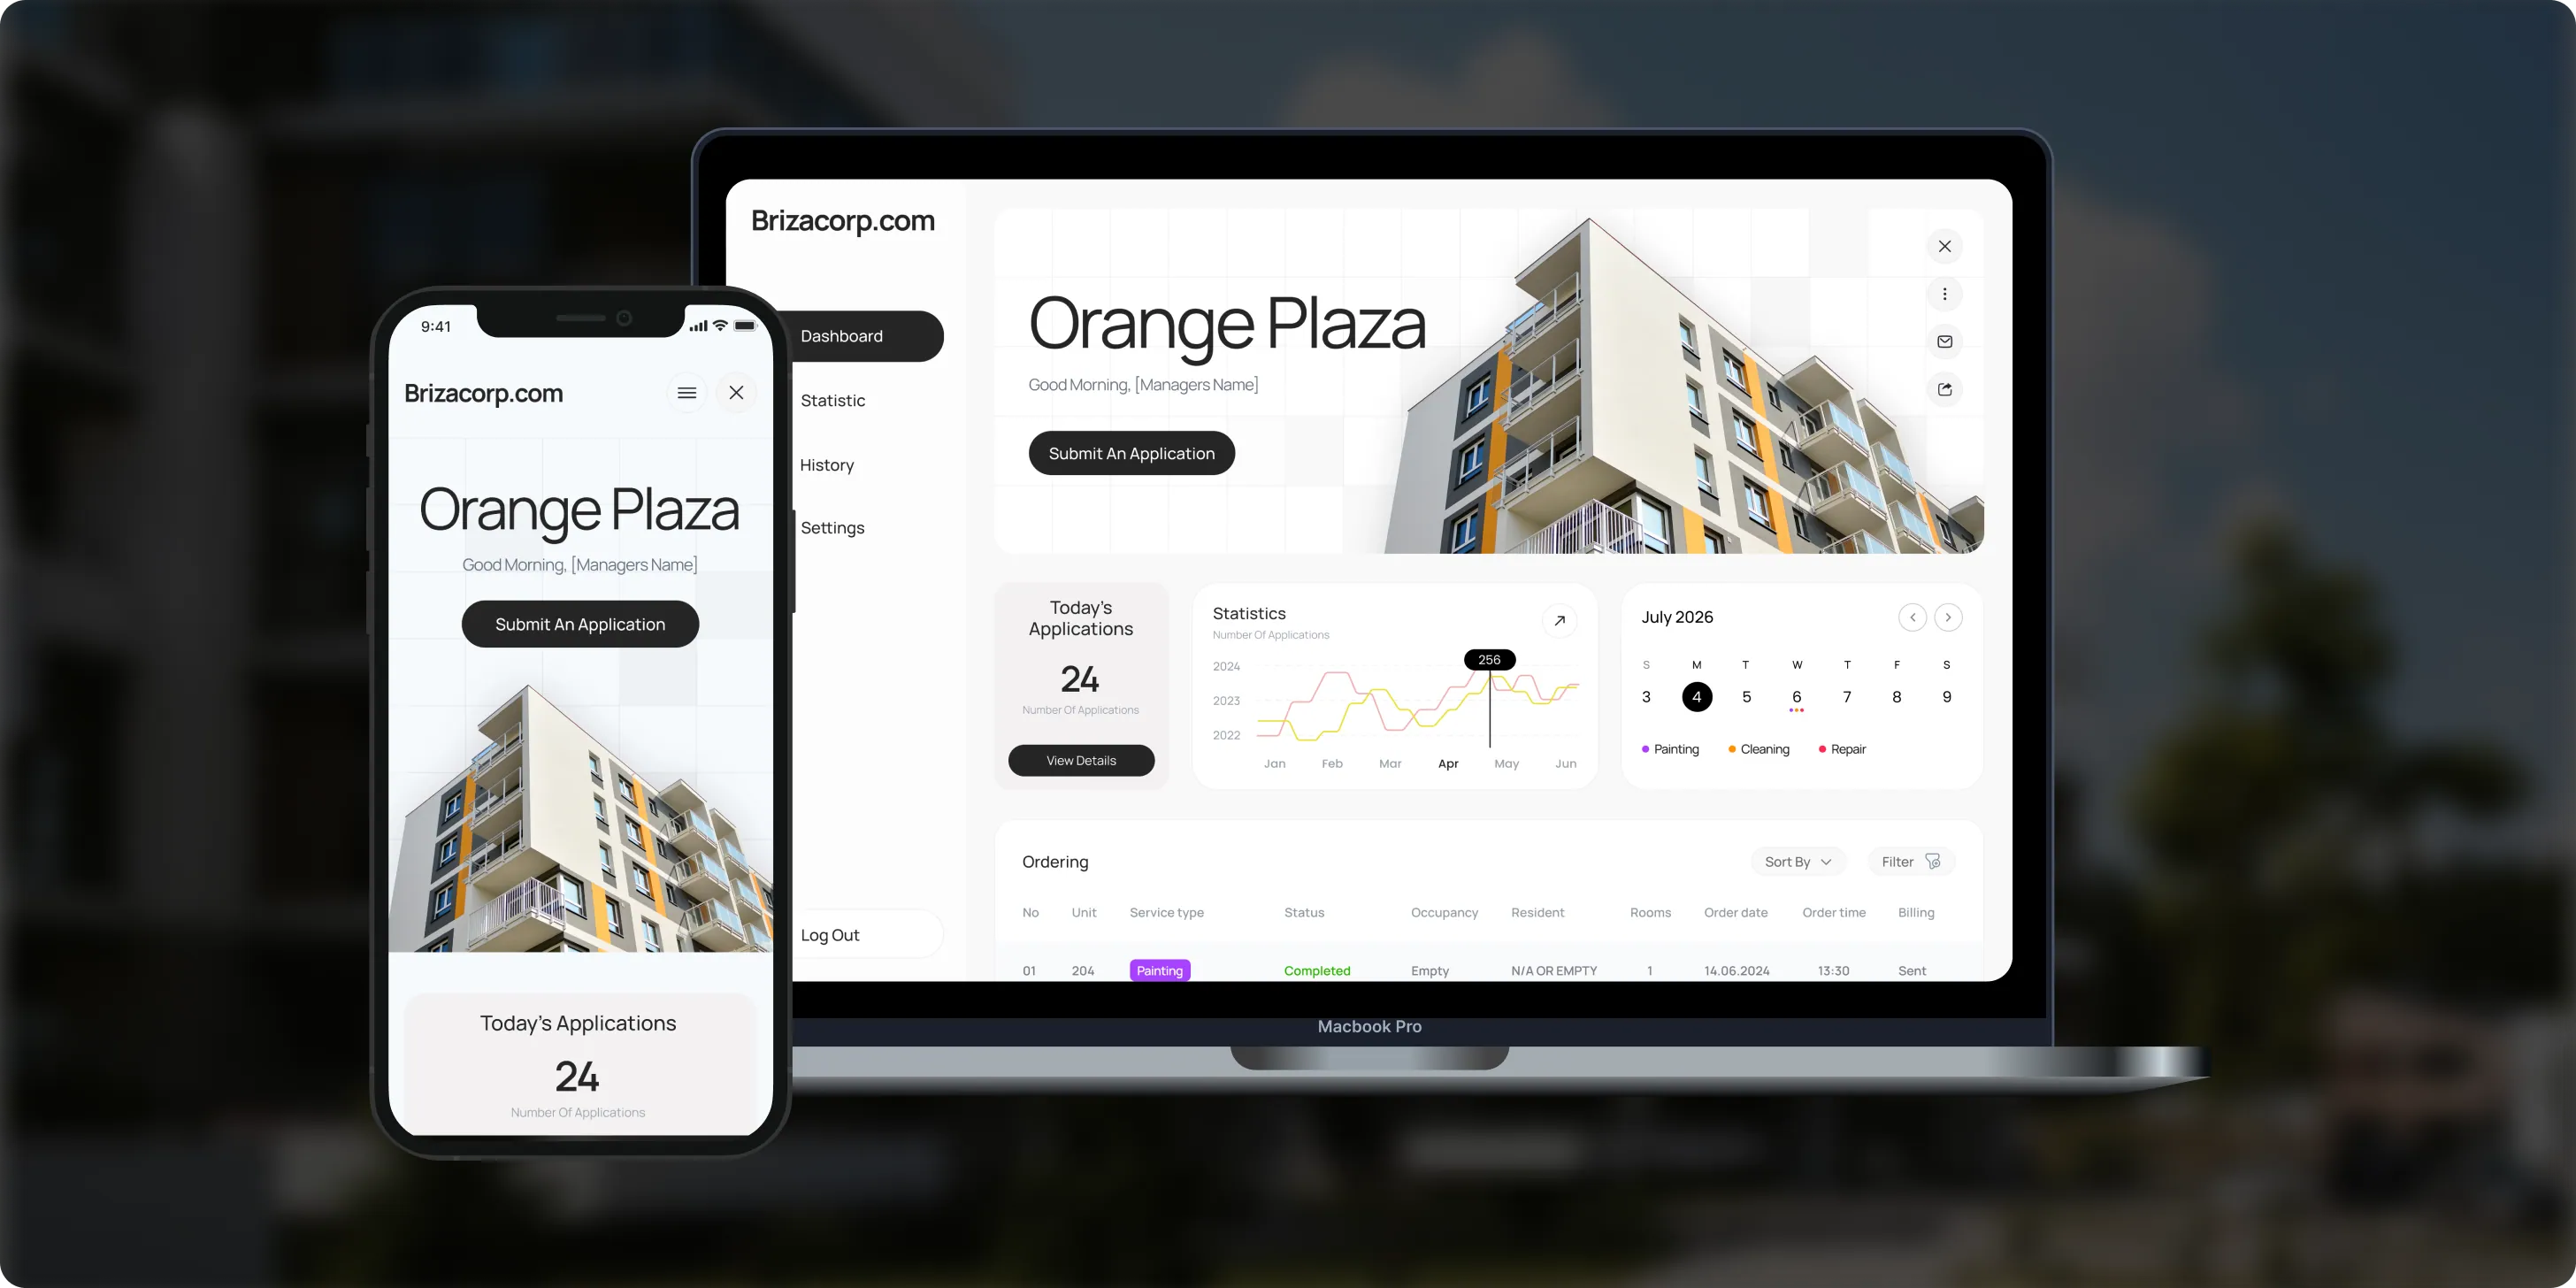
Brizacorp
Brizacorp manages residential properties and coordinates the staff who handle painting, cleaning, and repair requests. Its team tracked work across messengers, phone calls, e-mail, and paper planners, with no single place to manage requests or measure performance.- 98%Application Stability
- 95%Utilization Rate
- 30%Faster Task Completion
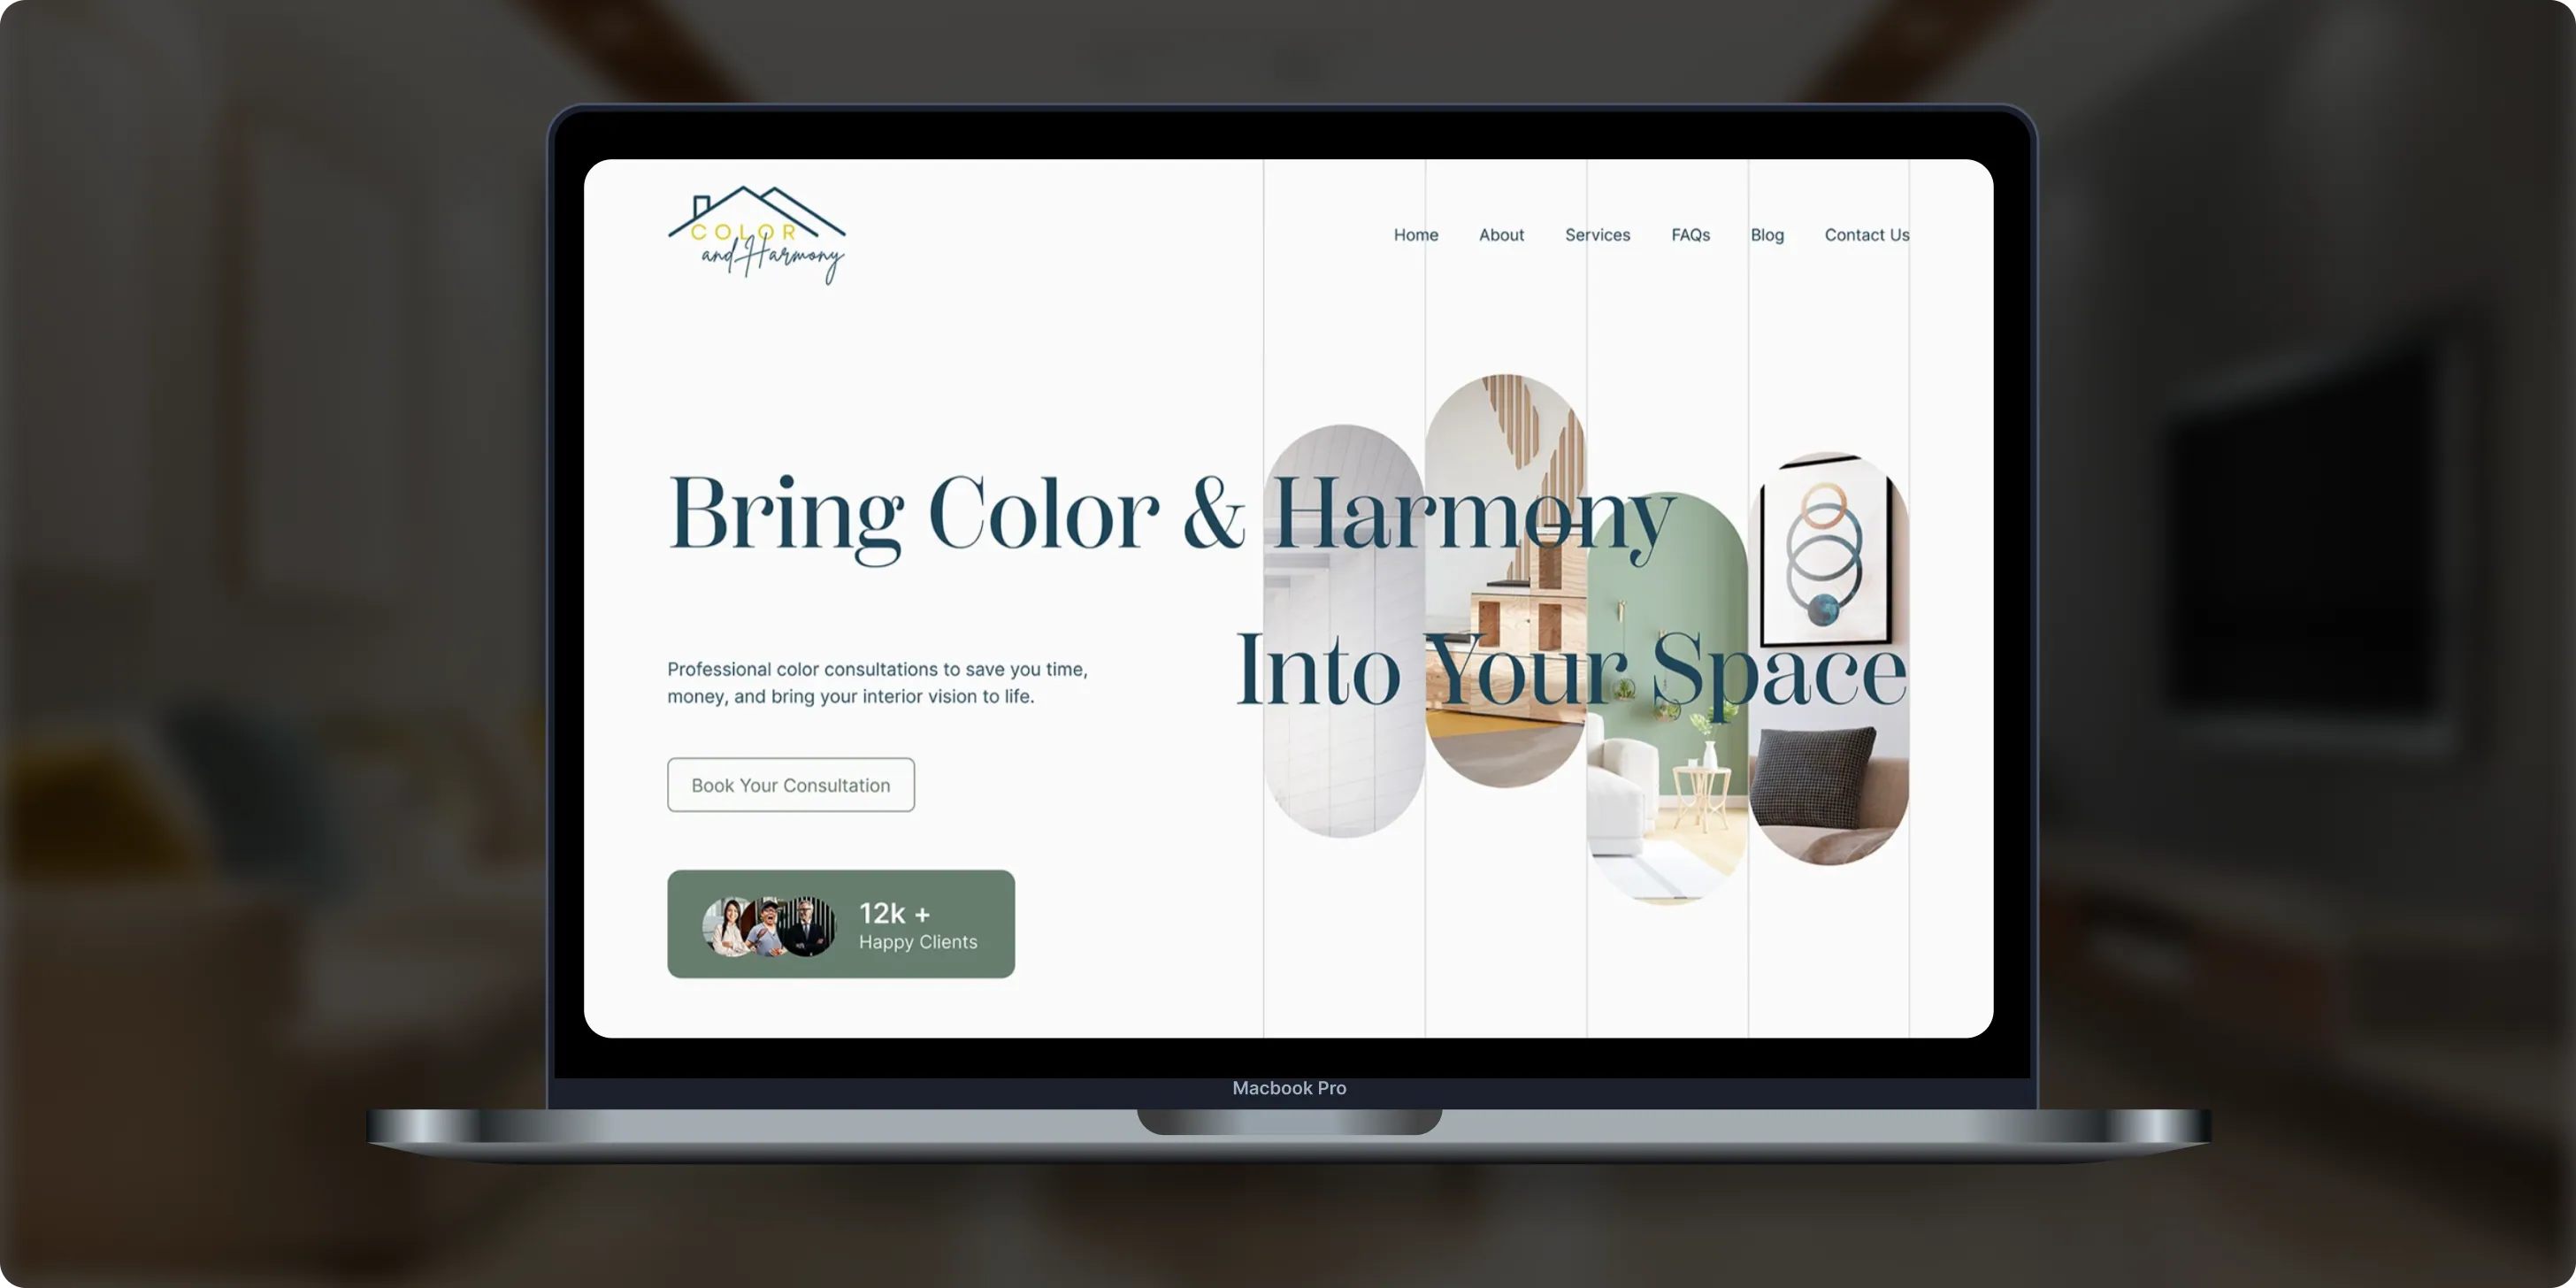
Color & Harmony
Color & Harmony is a Kentucky-based color consulting studio led by certified color strategist Diana Cartaya. The studio needed a website that reflects its refined aesthetic, showcases its portfolio, and explains a science-based color process in simple language.- 45%Conversion Rate Increase
- 50%Higher User Engagement
- 2Months to Launch
The Modern Gentlemen
The Modern Gentlemen sells premium men's skincare featured in Men's Health, GQ, and Men's Journal. Its customers wanted an efficient routine, but generic product suggestions and limited skincare knowledge made choosing the right products hard.- 30%Increase in Conversions
- 25%Higher Customer Retention
- 92%Mobile Purchases

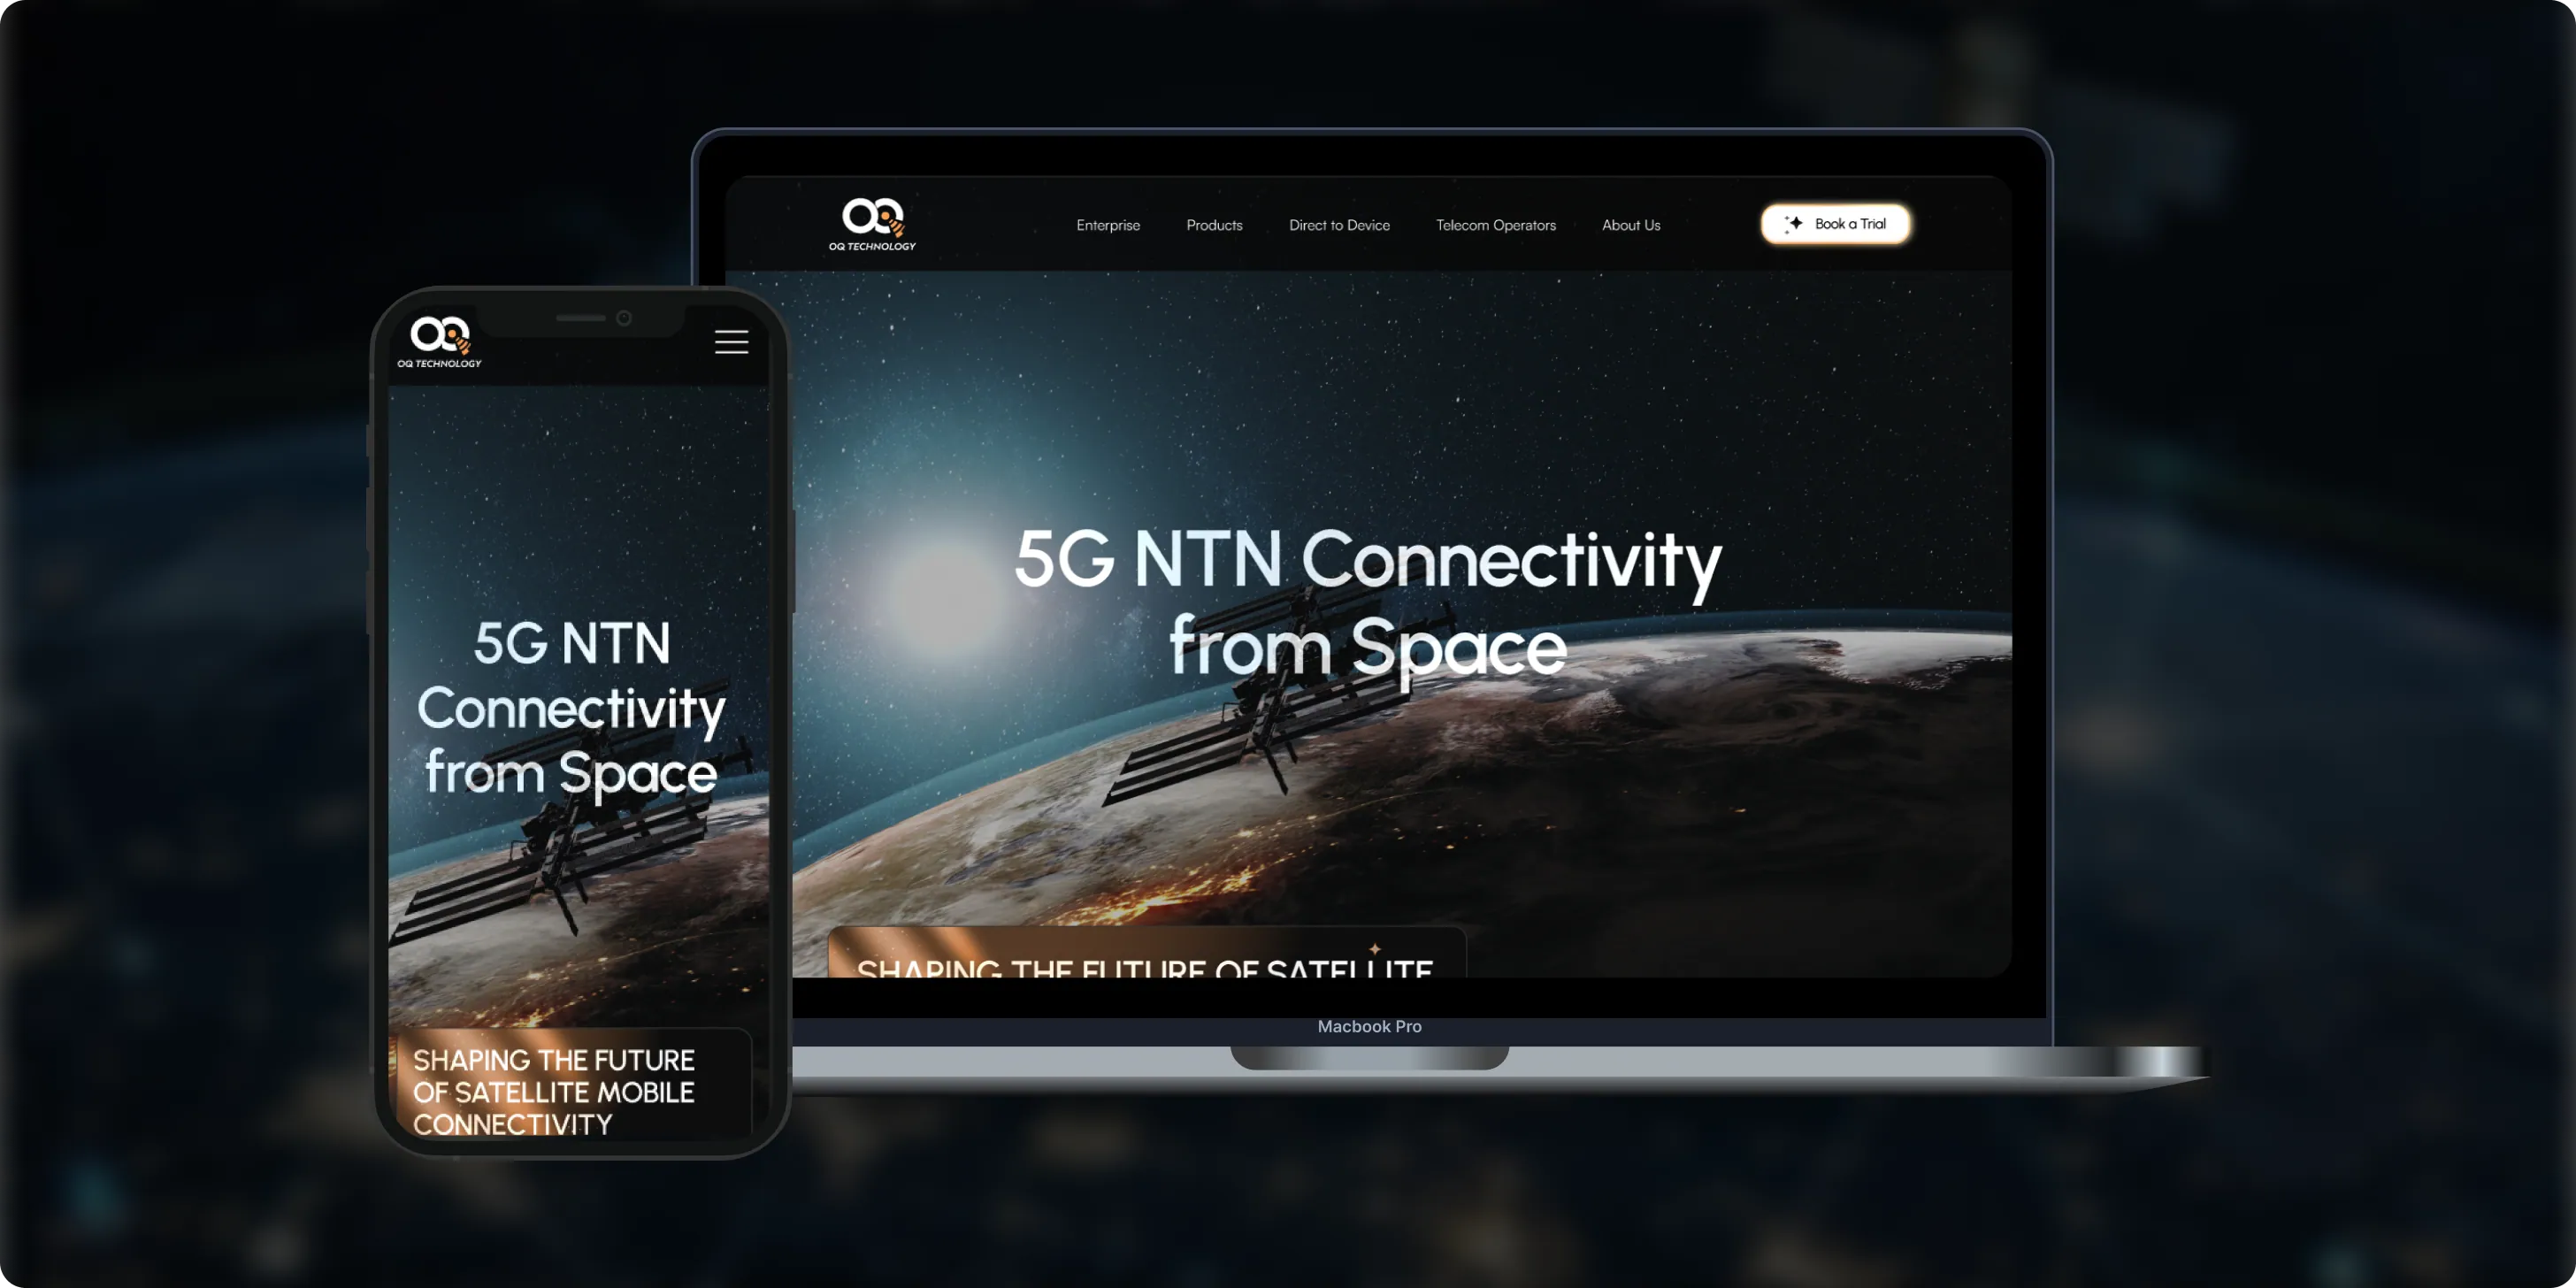
OQ Technology
OQ Technology connects IoT devices, machines, and people anywhere on the planet through its satellite network, serving energy, maritime, logistics, agriculture, and mobile operators. Its website made it hard to explore products and reach pricing plans.- 4Pricing Plans Clarified
- 3Dedicated User Flows
- 1Unified Platform
- Real Estate
- Finance
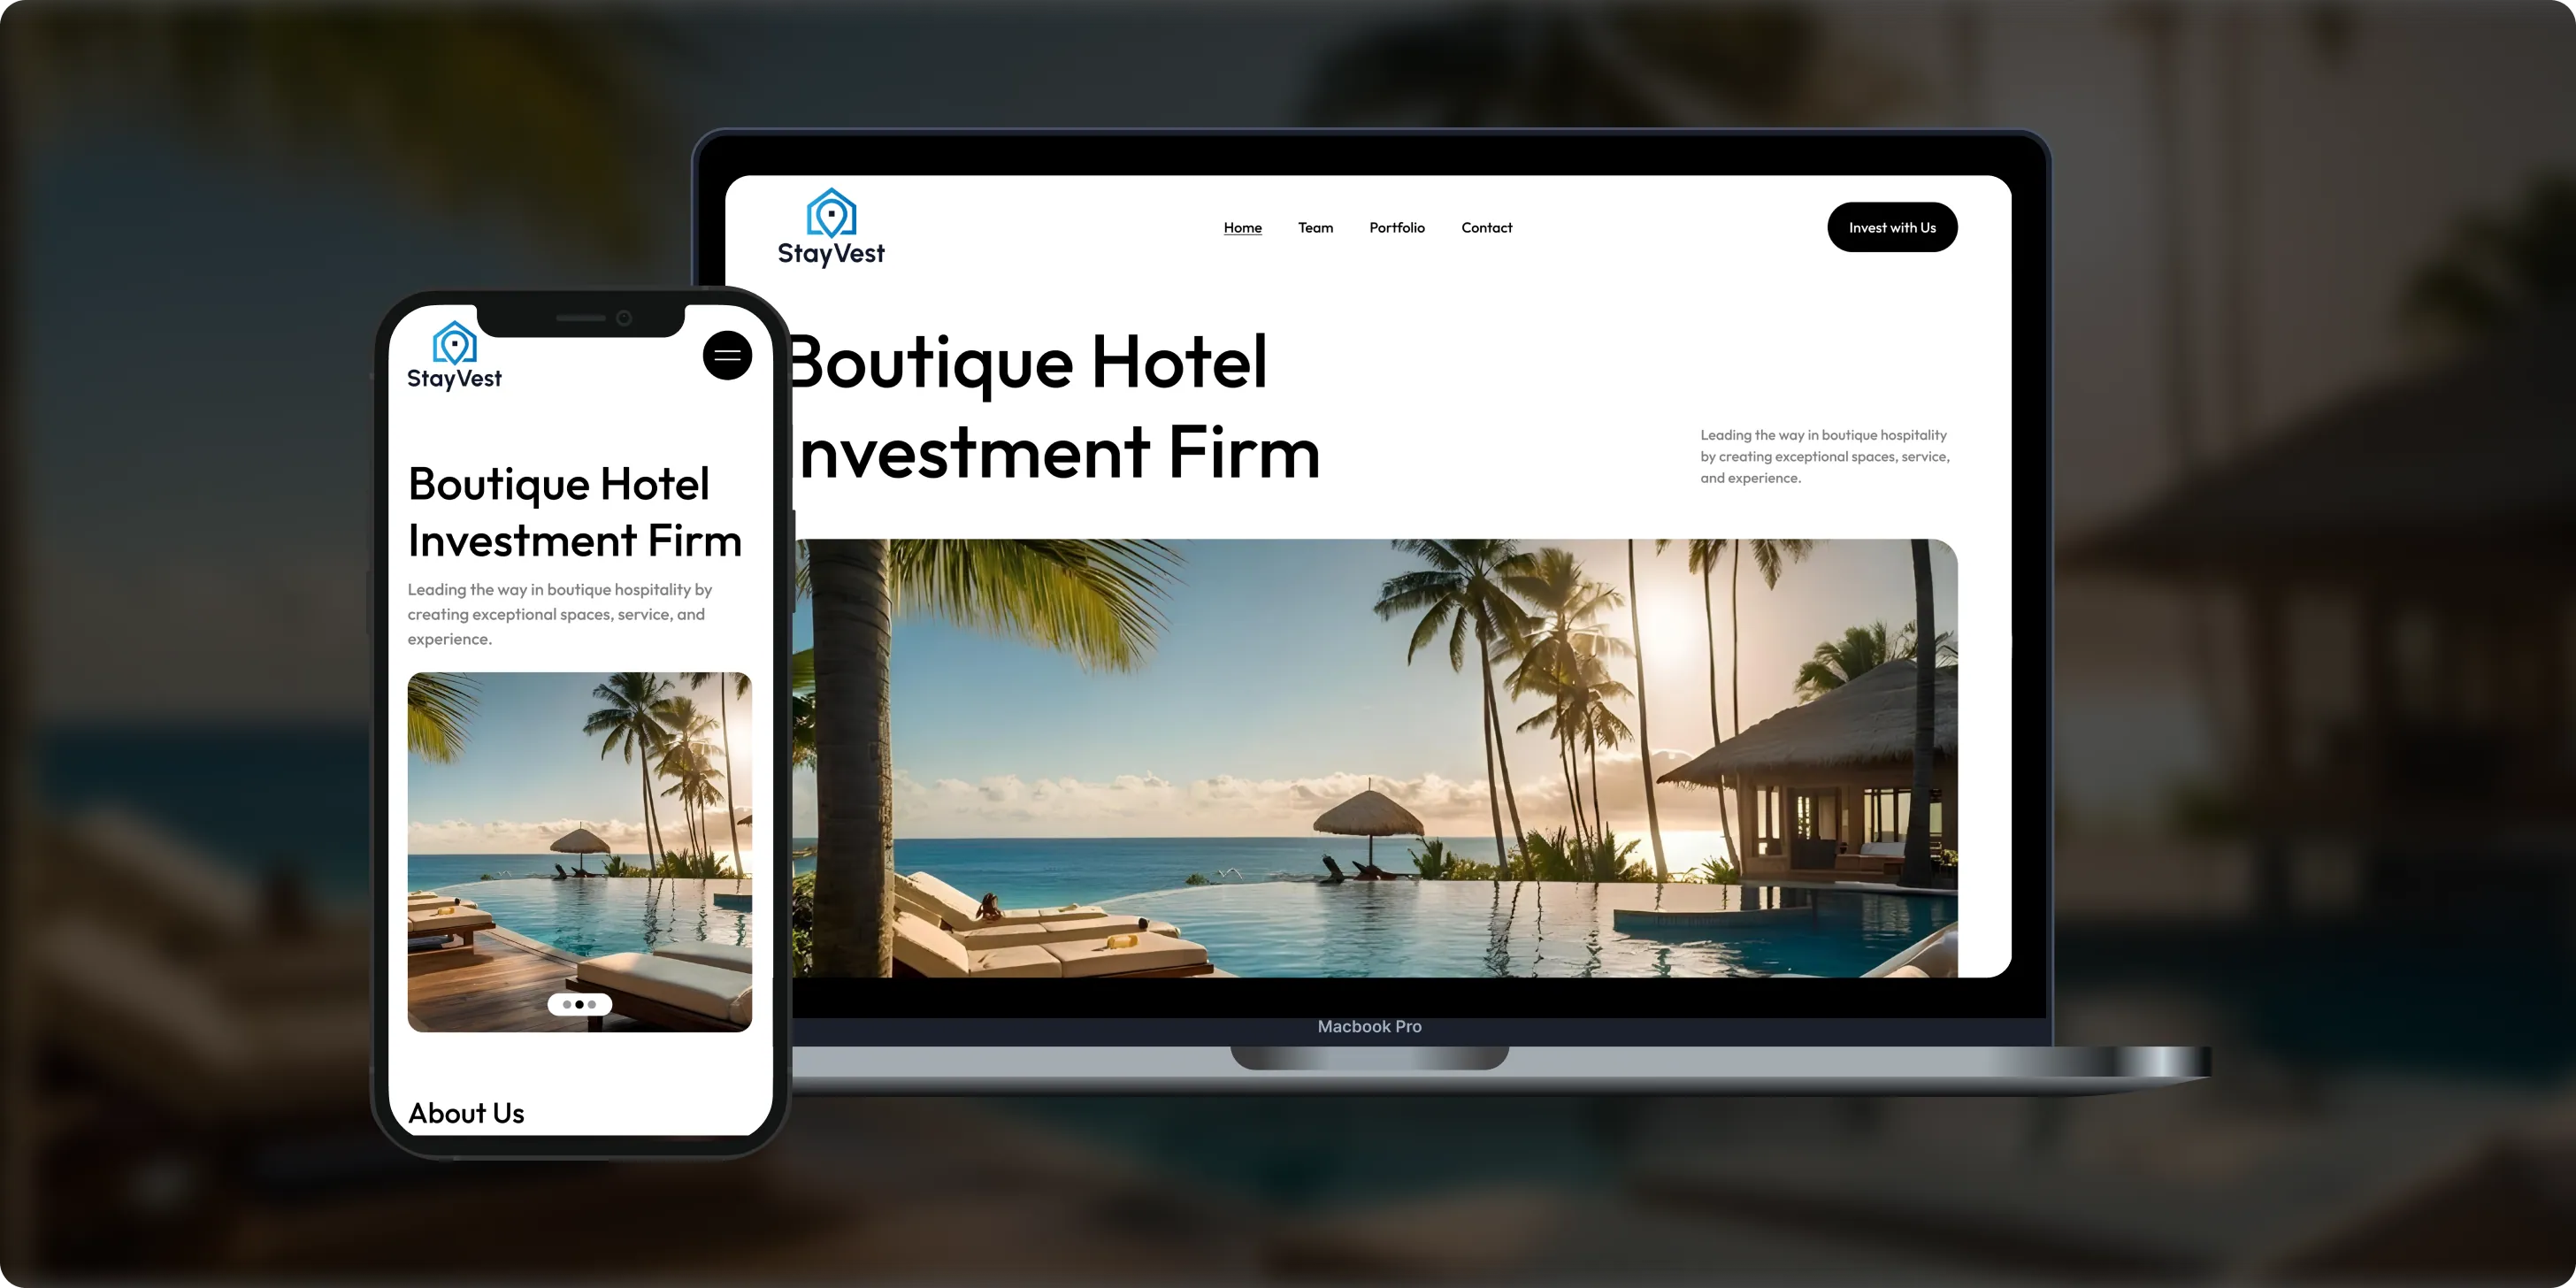
Stay Vest
Stay Vest is a private real estate investment firm that acquires, renovates, and operates boutique hotels for cash flow, tax benefits, and equity gain. It needed a platform that explains its strategy and earns the trust of passive investors.- 1,500+Guest Stays
- 200+Rooms Managed
- 5States Covered
Bokeyno Motorsports
Bokeyno Motorsports is the leading mobile installer of vertical doors for high-performance cars. This Shopify website isn’t just about services—it’s a bold statement of power, style, and expertise. With a sharp layout, strong visuals, and real-world case studies, the site delivers all the information car enthusiasts need to book confidently and instantly.- 54%Booking Requests
- 43%Lead Conversion
- 32%Qualified Inquiries

ai document processing platform
A comprehensive talent solution designed to help companies attract, hire, and retain top talent more effectively. The platform combines AI-powered recruitment technology with employee financial wellbeing programs, enabling smarter hiring decisions while supporting employees’ financial stability and long-term engagement.- 62%Faster Processing Time
- 78%Less Manual Work
- 35%Improved Accuracy

WHAT CLIENTS SAY
Independently verified reviews from real clients on Clutch.co


Client Story
Real feedback from
FMY Orthodontics

“Their perseverance and solution-oriented mindset. SoftDoes consistently found ways to make things work, added features we had not originally envisioned, and never became frustrated. It felt like working with a true partner who cared about the success of our practice.”
Dan Merwin
DDS, MS -- President, FMY Orthodontics

Client Story
Real feedback from
Prior Authorization AI
“Every time I sent a request, if there was anything that didn't work, they were able to turn it around quickly. Even when there were no updates yet, they always reached out to let me know they were working on it.”
Joseph Oluwo
Founder of Prior Authorization AI


Client Story
Real feedback from
WOVEN
“What stood out most was their commitment to understanding our needs before presenting solutions.”
Danna Pastran
Administrative Operations Manager, WOVEN

Client Story
Real feedback from
Grand Central Language Services
“The site performs as intended and provides the foundation for our company's digital presence.”
Joe Goldstein
QA Manager, Grand Central Language Services


Client Story
Real feedback from
DineMate
“They go above and beyond.”
Eric Snead
CEO, DineMate "Dating Connecting Platform"
Why they Choose SoftDoes
- 01SENIOR ENGINEERS, NOT LAYERS
Projects are led by senior engineers and architects who have shipped HIPAA-compliant healthcare integrations, revenue cycle tooling, and payer-side utilization management systems - not passed through layers of account managers. They can read CMS-0057-F, Da Vinci implementation guides, X12 278 specifications, state gold-carding statutes, and individual payer policies, then translate those requirements into domain models, APIs, and rules engines. Client revenue cycle, UM, clinical, and IT leads work directly with SoftDoes engineers, reducing the misinterpretation of requirements that plagues hand-off-heavy vendor models. Technical deep dives are routine: FHIR Coverage, Claim, and ClaimResponse resources, CRD/DTR/PAS flows, EHR integration constraints, rules engine architecture, and performance considerations at scale. This expertise shortens discovery cycles and yields designs that survive real-world payer behavior - not just idealized diagrams.
- 02PREDICTABLE DELIVERY
SoftDoes approaches prior authorization software development in phased releases: one specialty, service category, or line of business first, then expanding to more payers and prior authorization workflows once patterns are proven. Written specifications and acceptance criteria are tied to concrete PA scenarios - an urgent MRI, a planned surgery, a DME rental, a specialty drug, partial approvals, denials with appeals. Regular demos use synthetic patient data and, where available, payer test endpoints so stakeholders see end-to-end flows before go-live. SoftDoes coordinates dependencies with client IT, compliance, security, EHR vendors, clearinghouses, and payer partners to keep timelines honest. Predictable delivery matters because delays can derail CMS reporting timelines - new operational requirements take effect January 1, 2026, and API compliance is due by January 1, 2027 - and force clinics back to manual processes that cost physician and staff time.
- 03BUILT TO LAST PAST LAUNCH
SoftDoes designs prior authorization systems as modular services with clear domain boundaries: coverage, orders, requests, documents, decisions, and appeals each have defined contracts and can evolve independently. Observability is built in: structured logging, metrics on queue times and SLA adherence, integration health checks for each payer channel, and alerting for stuck or failed PA submissions so problems surface before they cause missed deadlines or delayed patient care. Maintainability practices include peer code reviews, automated tests on rules engines and decision timers, regression suites for critical integrations, and CI pipelines with static analysis and security scanning. The architecture is sized so growth in authorization volume, new participating payers, and additional service types do not require constant rewrites - and design decisions aim for multi-year adaptability as CMS rules, FHIR versions, and payer policies evolve.
- 04NO BABYSITTING REQUIRED
Onboarding includes admin training, runbooks, and structured knowledge transfer so internal authorization champions can operate and extend the system confidently from day one. Admin consoles surface key configurations - payer rule sets, service catalogs, documentation checklists, queue routing, SLA timers, user and role management, and integration-status dashboards - in interfaces designed for operations staff, not engineers. Clear boundaries separate what client IT can change safely from where SoftDoes support is recommended, avoiding both reckless changes and unnecessary vendor tickets. SoftDoes offers ongoing partnership options for organizations that want them, but every system is built so clients are not dependent on the vendor for day-to-day operations. The goal: your team can adjust recurring authorizations, add a new payer's documentation requirements, or update routing rules without waiting on anyone.
How we work with your quality team
This is how SoftDoes partners with you from first conversation through long term support.




Experience Across Providers, Health Plans, and Revenue Cycle Teams
We build prior authorization software where faster approvals, CMS compliance, and a clear audit trail are non-negotiable.
Dental Practices
Patient Portal
EHR/EMR
Telemedicine
RPM Software
Complex systems, integrations, and internal platforms built to evolve. We step in when off-the-shelf tools stop being enough.
Healthcare
From first version to real traction without painting yourself into a corner. Built for speed now and hard decisions later.
Healthcare CRM
Systems designed around controls, traceability, and change management. Built so audits don’t become fire drills.
Medical Billing
Infrastructure software built for long timelines and high stakes. Reliable systems for assets that can’t afford guesswork.


Frequently Asked Questions
Everything you need to know about working with SoftDoes. Can’t find an answer?
How long does a custom prior authorization software development project take, and what drives the cost?
A focused provider-side module - for example, authorization tracking and electronic submission for a single specialty - can reach initial release in three to five months. A full end-to-end prior authorization platform with requirement checks, multi-channel submission, review workflows, appeals, and analytics typically takes nine to eighteen months, depending on the number of payer integrations and regulatory scope. The main cost drivers are the number of EHR and payer system integrations, complexity of payer rules and clinical criteria licensing (InterQual, MCG), AI components, and compliance requirements such as CMS-0057-F, URAC, and NCQA. Payer testing cycles, internal decision-making, and staff training often influence total duration as much as engineering effort.
How does the software help with the CMS Interoperability and Prior Authorization rule (CMS-0057-F)?
Prior authorization software ensures compliance with federal mandates such as CMS interoperability rules by embedding decision timers (seven days for standard requests, 72 hours for expedited requests), structured denial reasons, public reporting of prior authorization metrics, and FHIR-based APIs for prior authorization, provider access, and payer-to-payer data exchange. On the provider side, systems consume FHIR PAS endpoints and expose necessary clinical data so clients benefit from faster electronic decisioning - automated submission of prior authorization requests can improve revenue cycle management across the board. SoftDoes works closely with each client's compliance team, which retains responsibility for interpreting the rule and defining internal policies; SoftDoes implements those interpretations in software. Support for Da Vinci CRD, DTR, and PAS means future CMS or commercial payer requirements can be met without another ground-up rebuild.
Can you integrate with our EHR, clearinghouse, and payers?
Integration is a core part of every prior authorization software project. SoftDoes uses FHIR and SMART on FHIR for EHR integration - allowing automatic data retrieval of patient demographics and clinical notes - X12 278 through clearinghouses, payer FHIR APIs, and pharmacy ePA networks where available. Data mapping between systems covers patients, coverage, orders, authorizations, and decisions, with real-time status updates, robust error handling, retries, and fallbacks when a payer channel is unavailable. SoftDoes has delivered integrations with Epic, Oracle Health, athenahealth, eClinicalWorks, Availity, Change Healthcare/Optum, Waystar, CoverMyMeds, Surescripts, and custom payer platforms - all without disrupting scheduling or billing.
How do you keep patient data secure and compliant?
SoftDoes designs prior authorization software with HIPAA and security best practices from the foundation: encryption of PHI at rest and in transit, minimum-necessary data sharing, role-based access controls, multi-factor authentication options, and detailed audit logs capturing every request, decision, and action. Strong auditing and security controls are essential for protecting patient information in PA systems. Projects typically include a HIPAA risk analysis, secure coding practices, and collaboration with client security teams on threat modeling and penetration testing, aligned with frameworks used in SOC 2, HITRUST, or ISO 27001 contexts. SoftDoes signs appropriate BAAs when handling PHI as part of the engagement.
Who owns the source code, rules, and intellectual property?
For custom prior authorization software, clients typically own the source code, configuration, and payer rules developed for them, subject to the services agreement. Third-party components - licensed clinical criteria content such as InterQual or MCG, ePA network connections, or integration middleware - remain under their own licenses, with clear documentation of what is bespoke versus shared. Standard open-source libraries and SoftDoes internal utilities may be reused across projects, also documented transparently. At handover, clients receive repositories, technical documentation, and deployment artifacts needed to operate and extend the system independently.
Should we build custom prior authorization software or buy an off-the-shelf tool?
Off-the-shelf authorization tools can work well for organizations with straightforward authorization patterns, a limited payer mix, and minimal integration needs - they are the fastest to deploy. Custom prior authorization software development makes sense when the payer mix is complex, specialties have unusual medical necessity criteria or documentation requirements, the organization has payer-side regulatory obligations, deep EHR or core-system integration is essential, or the goal is building a commercial health IT product. SoftDoes often helps clients extend existing tools - adding FHIR APIs, AI document review, or bespoke analytics on top of what is already in place - rather than replacing everything on day one. Part of discovery is an honest build-versus-extend assessment to reduce risk and cost.
Can AI make prior authorization decisions?
AI should support, not replace, qualified clinicians and UM staff for prior authorization decisions - especially denials. AI prior authorization tools can assemble evidence, check completeness, surface guideline matches, and recommend approvals in straightforward cases, all with human oversight and explainable outputs. AI-driven platforms can prepare complete submissions in under a minute, and AI can handle 50–75% of manual tasks in prior authorization, but configurable thresholds ensure auto-approval only fires under payer-defined rules, with every AI rationale logged for audits. SoftDoes monitors models for accuracy and bias, and designs systems so adverse decisions always remain with licensed clinicians - never the model alone.
How do you reduce risk on a complex prior authorization initiative?
Phased rollouts by specialty, service type, or payer are the primary risk-reduction strategy, combined with proofs of concept for the riskiest integrations - like a payer's untested FHIR sandbox or a legacy clearinghouse connector - before full-scale build-out. SoftDoes relies on automated regression tests, payer test environments, and parallel runs with existing processes during cutover so that 82% of clinicians who report patients abandon treatment due to PA complexity are not further harmed by a rocky transition. Clear rollback plans and hypercare periods after go-live focus on the most critical failure modes: stuck requests, expiring authorizations, and missed SLA deadlines. Transparent communication on tradeoffs - what must change operationally versus what can be automated - ensures leadership can make informed decisions throughout the project.


